
Anterior Cruciate Ligament (ACL) Rupture
Updated: Apr 8
Anterior cruciate ligament (ACL) injuries most often occur during sudden changes in direction, trunk rotation on a fixed foot, or incorrect landing mechanics . A significant number of patients describe a "tearing" or "popping" sensation inside the knee at the moment of rupture. The rapidly developing swelling that follows is usually due to intra-articular bleeding (hemarthrosis).
However, clinically, the primary determining factor is not pain, but instability. While pain and swelling are prominent in the early stages, patients later report a feeling of the knee "giving way," a lack of confidence, and loss of control, especially during rotational movements. This demonstrates that the cruciate ligament is not merely a passive ligament, but a central component of the knee's dynamic stability system.
The ACL is the primary structure that limits the anterior translation of the tibia over the femur, meaning it prevents the tibia from sliding forward relative to the upper leg. However, its function is not limited to preventing anterior sliding; it plays a crucial role in the rotational stability of the knee. Therefore, the problem after a rupture is a loss of three-dimensional control.

Image reference: https://orthoinfo.aaos.org/en/diseases--conditions/anterior-cruciate-ligament-acl-injuries/
LONG-TERM CONSEQUENCES OF CRUCIATE LIGAMENT INSUFFICIENCY
The literature reports an increased risk of meniscus injury in patients with ruptured cruciate ligaments . Meniscus tears are particularly common when treatment is delayed.
These findings demonstrate that ACL injury is not merely a ligament injury, but a process that affects joint biology and long-term joint health.
LACHMAN TEST: PHYSICAL DIAGNOSIS OF ANTERIOR CRUCIATE LIGAMENT RUPTURE
The Lachman test is one of the most reliable physical examination methods for evaluating anterior cruciate ligament tears . It is performed with the knee bent (flexion) at approximately 20–30 degrees. In this position, the physician stabilizes the femur (upper leg) and assesses the forward displacement of the tibia (lower leg).

Image reference: https://coreem.net/core/acl-injuries/
An intact ACL restricts anterior movement of the tibia and provides a clear sense of limitation. If the ligament is torn, the tibia moves further forward, and this sense of limitation is lost. The biggest advantage of the test is that it can be performed even immediately after the injury and is less affected by muscle spasm compared to other tests.
Therefore, the Lachman test is considered one of the cornerstones of clinical evaluation in cruciate ligament injuries.
ANTERIOR CRUCIATE LIGAMENT TREATMENT: DOES EVERY CRUCIATE LIGAMENT RUPTURE REQUIRE SURGERY?
Treatment decisions for anterior cruciate ligament tears are not based solely on imaging findings. The main determining factors are the patient's age, activity level, and expectations for the knee.
The approach commonly used in clinical practice can be roughly summarized as follows:
Surgical reconstruction is often preferred in active individuals under 40 (especially those who participate in active sports). This is not solely due to the return to sports. In young and active knees, repetitive instability can increase the risk of meniscus and cartilage damage, which can lead to premature degeneration (wear and tear) in the long term. Therefore, restoring the mechanical stability of the knee in this age group is generally a safer strategy.
In individuals over 50 , the approach is more cautious. Most patients in this group do not engage in high-level rotational sports and may not experience significant instability during daily living activities. If the knee is not "giving way," muscle control is good, and there are no accompanying serious meniscus problems, non-surgical treatment is often sufficient.
The 40-50 age group is where treatment decisions are most individualized. Here, biological age, activity level, occupation, sports habits, and the degree of instability complaints are more decisive than chronological age. The treatment approach may not be the same for a 45-year-old marathon runner and a 45-year-old inactive individual.
WHAT DOES CONSERVATIVE TREATMENT MEAN?
Non-surgical treatment is not "doing nothing" .
The conservative approach;
Control of edema and inflammation.
Quadriceps and hamstring strengthening
Neuromuscular balance training
Proprioception studies
Use of knee braces if necessary.
This includes a structured rehabilitation program.
The goal is to partially compensate for the torn ligament through muscle control. A strong and coordinated muscle structure significantly contributes to knee stability. However, this approach cannot fully restore the mechanical function of the ligament in activities requiring high-level pivoting and sudden changes of direction.
Therefore, the choice of treatment depends on the following question:
To what level of knee use does the patient want?
The decision should be based not only on the MRI image but also on the patient's lifestyle. And when the right patient is selected, both surgical and conservative approaches can be successful.
HOW IS CRUCIATE LIGAMENT SURGERY PERFORMED: RECONSTRUCTION
The most natural question regarding anterior cruciate ligament injuries is: "If the ligament is torn, why isn't it just stitched?"
This question is logical. Because in everyday life, a torn piece of fabric can be sewn, a ripped tissue can be repaired. However, the knee joint is not such a simple system.
In the past, attempts have indeed been made to "repair" the ligament. From the late 19th century onwards, surgeons tried to reattach a torn anterior cruciate ligament, and this method was widely used for a time. However, long-term results have not been satisfactory. Re-rupture rates within five years have been reported to be over 50%. The main reason for this is the limited blood circulation in the anterior cruciate ligament and the unfavorable intra-articular environment for healing. The knee joint is a constantly moving, weight-bearing structure filled with synovial fluid. This environment often does not allow for permanent healing with a simple suture.
Therefore, the approach has changed over time.
In modern understanding, instead of stitching a torn and dysfunctional ligament, it is reconstructed. This is called "reconstruction." The goal is to restore the mechanical control the knee has lost. What is done here is to rebuild the knee's central stabilizer. Often, a piece of tendon (such as the gracilis or semitendinosus) taken from the patient's own tissue is used. This new structure adapts to the body over time, receives blood supply, and undergoes biological transformation.
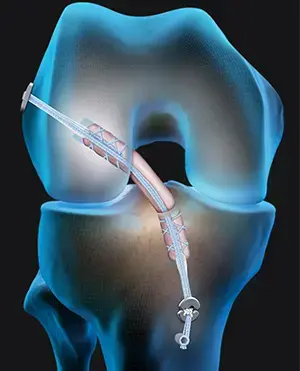
Image reference: https://www.momayamd.com/acl-reconstruction-orthopedic-sports-medicine-specialist-birmingham-huntsville-montgomery/
The goal of this surgery is not just to get the patient back to sports. The aim is to preserve the long-term biomechanics of the knee. Because if the patient continues with a torn cruciate ligament, the risk of meniscus and cartilage damage increases. This can pave the way for early osteoarthritis in the future.
THE IMPORTANCE OF POST-OPERATIVE REHABILITATION
The most common mistake in cruciate ligament surgery is believing that surgery is the central focus of the process. However, surgery is only a mechanical beginning. The main factor determining functional outcomes is rehabilitation. Significant quadriceps muscle weakness can develop both after trauma and after surgery.
Postoperative rehabilitation progresses in three main stages:
Maintaining range of motion , especially achieving full extension early, is critically important.
Muscle strength must be regained , and the balance between quadriceps and hamstrings must be re-established.
Neuromuscular control and balance require the knee to be not only strong but also controlled.
Return to sport should be determined by functional criteria, not by time. Early return without evaluating muscle strength symmetry, balance tests, and movement control can increase the risk of relapse.
In short, successful ACL treatment requires a disciplined and patient rehabilitation process.
IS THERE A GOLD STANDARD IN TREATMENT?
Today, ACL reconstruction is considered the main approach to treatment. However, the "one right way for every patient" approach is not accurate.
There are three main factors that determine the treatment decision:
Patient's age and activity level
Presence of knee instability.
Long-term joint health goal
In young and active individuals, surgery is often the safest option. For patients with lower activity levels, well-structured conservative treatment may suffice. However, it must be clearly stated: a cruciate ligament injury is not just a ligament problem. It is a condition requiring the biomechanics of the knee to be restructured. Surgery alone is not a miracle cure. Success is incomplete without rehabilitation. The risk of complications increases if the timing is wrong. Ultimately, success is a combination of the right patient selection, the right timing, and disciplined process management.
Anterior cruciate ligament (ACL) treatment is not an operation, it's a strategy.
References:
Shom P, Varma AR, Prasad R. The Anterior Cruciate Ligament: Principles of Treatment. Cureus 2023 Jun 11;15(6):e40269. doi: 10.7759/cureus.40269. PMID: 37448400; PMCID: PMC10336184.
https://orthoinfo.aaos.org/en/diseases--conditions/anterior-cruciate-ligament-acl-injuries/


Comments