
Shoulder dislocation: mechanism, symptoms, and treatment
Updated: Apr 8
The shoulder joint is the joint with the widest range of motion in the human body . Many movements, such as raising, extending, rotating, or moving our arm backward, are possible thanks to this joint. However, this great freedom of movement also makes the shoulder joint more unstable , meaning it is more prone to dislocation.
Therefore, shoulder dislocation is the most common type of dislocation among all joint dislocations .
Medically, a dislocated shoulder means that the head of the humerus , the rounded structure at the top of the arm bone, completely separates from the glenoid cavity (shoulder socket) above the scapula .
Shoulder dislocations can occur in different directions, but the most common form is traumatic anterior shoulder dislocation . In this case, the head of the humerus dislocates forward from the joint socket . Traumatic anterior dislocations account for approximately 80–90% of all shoulder dislocations .
This injury typically results from traumatic events such as impacts during sports, excessive external rotation, falls, and traffic accidents.
Epidemiological data indicate that the annual incidence of traumatic anterior shoulder dislocation is approximately 11–29 cases per 100,000 people .
SHOULDER ANATOMY AND STABILITY
The shoulder joint is called the glenohumeral joint . This joint consists of two main structures:
Head of the humerus: The rounded structure at the top of the humerus (upper arm bone).
Glenoid cavity: The shallow articular surface located on the scapula (shoulder blade).
This structure functions like a ball-and-socket system. However, unlike the hip joint, the socket in the shoulder joint is quite shallow. This means the humeral head does not sit very deeply within the glenoid cavity. While this allows for a wider range of motion in the shoulder, it also makes the joint more prone to instability .

Shoulder stability is provided by two main mechanisms :
1) Static stabilizers
Static stabilizers are structures that hold a joint in place even without movement .
Static stabilizers:
Glenoid labrum
joint capsule
Glenohumeral ligaments
The labrum is a cartilage-like ring surrounding the glenoid cavity . This structure deepens the joint socket, helping to keep the humeral head within the joint. The joint capsule and ligaments are connective tissue structures surrounding the joint that control joint movement.

Image source: https://www.physio-pedia.com/Glenohumeral_Joint
2) Dynamic stabilizers
Dynamic stability is provided by the muscles. These muscles prevent joint dislocation by holding the humeral head within the glenoid cavity during movement.
The most important of these muscles is the rotator cuff muscle group .
Rotator cuff muscles:
supraspinatus
infraspinatus
teres minor
subscapularis
These muscles work together to stabilize the shoulder joint and allow for controlled arm movement.

Image source: https://www.physio-pedia.com/Glenohumeral_Joint
MECHANISM OF TRAUMATIC SHOULDER DISLOCATION AND OTHER ACCOMPANYING INJURIES
Traumatic anterior shoulder dislocation usually occurs as a result of a sudden force applied to the arm in a specific position.
The most classic mechanism:
This is a traumatic force applied while the arm is in abduction (lateral opening) and external rotation (outward rotation) positions. In this situation, the humeral head is forced towards the anterior edge of the glenoid cavity and eventually dislocates from the joint socket.

During this process, some structures that provide shoulder stability may be damaged. The most common injuries are:

Bankart lesion
A Bankart lesion is a rupture of the labrum in the anteroinferior portion of the glenoid cavity . Because the labrum plays a vital role in shoulder stability, this injury can lead to repeated shoulder dislocations.
Hill-Sachs lesion
A Hill-Sachs lesion is a depression-type bone defect that occurs in the posterior part of the humeral head . During dislocation, the humeral head strikes the glenoid edge, causing a depression in the bone. Hill-Sachs lesions play an important role in the assessment of shoulder instability because large defects can increase the risk of re-dislocation .
Rotator cuff injuries
Rotator cuff muscles can also be injured during shoulder dislocations.
The rotator cuff is a vital muscle group that provides shoulder stability. Tears in these muscles are more common, especially in older patients . Studies indicate that rotator cuff injuries may account for approximately 30% of shoulder dislocations.
EPIDEMIOLOGY - WHO IS MORE LIKELY TO GET SHOULDER DISLOCATIONS?
Traumatic anterior shoulder dislocation is a fairly common injury among orthopedic traumas. Studies show that the annual incidence of this injury is approximately 11–29 cases per 100,000 people .
However, this injury does not occur equally in all age groups. There are two distinct age groups for shoulder dislocations :
1) Young Adults
The first age peak is usually seen between the ages of 20 and 29 .
Shoulder dislocations in this age group:
mostly in men
often as a result of sports injuries
It emerges.
Contact sports are particularly risky. Examples include football, basketball, rugby, and combat sports.
It can be given.
During these sports, the shoulder joint can be subjected to high energy, and forces applied while the arm is in an abduction-external rotation position can cause shoulder dislocation.
2) Advanced Age
The second most common cause of shoulder dislocations is after the age of 60 .
In this age group:
Shoulder dislocations usually result from falls.
mostly in women
It is seen.
In older individuals, decreased muscle strength, balance problems, and changes in bone density can make these injuries more likely to occur. Furthermore, shoulder dislocations are more frequently accompanied by other injuries such as rotator cuff tears in this age group.
APPREHENSION TEST
Various clinical tests are used to assess shoulder instability. One of the most important of these is the apprehension test .
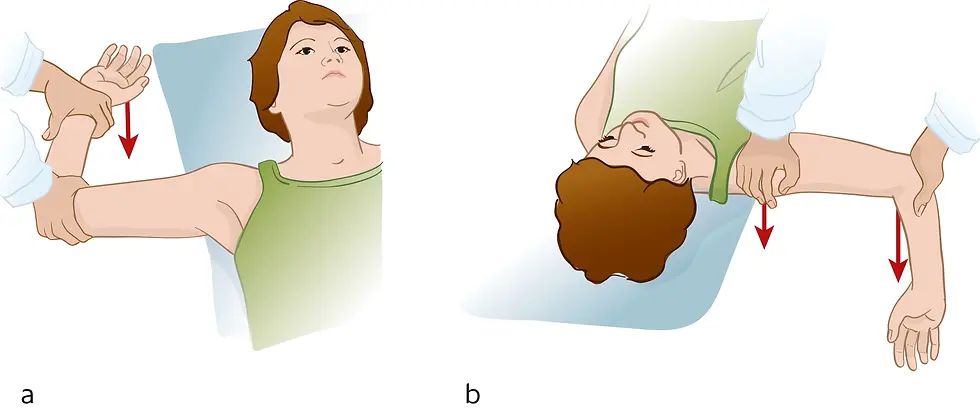
Image source: https://samarpanphysioclinic.com/apprehension-test/
During this test:
The arm is brought to approximately a 90° abduction position.
shoulder is forced into external rotation
Force is applied to the humeral head from the front.
The test is considered positive if the patient feels their shoulder is about to dislocate again in this position and involuntarily tenses their muscles . Studies show that a positive apprehension test increases the risk of recurrent shoulder dislocation by approximately four times in the future .
FIRST AID FOR TRAUMATIC SHOULDER DISLOCATION
Traumatic anterior shoulder dislocation is an orthopedic injury requiring urgent evaluation and rapid intervention . Patients typically present with sudden onset of severe shoulder pain, marked deformity of the shoulder contour, and inability to move the arm. While this clinical picture often suggests dislocation, the diagnosis should be confirmed with clinical evaluation and imaging methods .
The primary goal of shoulder dislocation treatment is to reposition the humeral head back into the glenoid cavity as quickly as possible. Prolonged dislocation can lead to increased muscle spasms and complicate the reduction process. Furthermore, delayed reduction can increase the risk of nerve and blood vessel injury. Therefore, traumatic shoulder dislocations are considered an emergency in clinical practice, and reduction should be performed without delay when appropriate conditions are met.
REDUCTION (FITTING INTO PLACE)
Reduction is the process of repositioning the humeral head back into its joint socket. In most cases, this procedure can be performed using a minimally invasive technique, meaning it doesn't require surgery . However, because pain and muscle spasms can complicate the reduction , analgesics, sedation, or muscle relaxants are usually used .
Various techniques have been described for shoulder reduction. The most commonly used methods include traction-countertraction techniques, the Stimson method, and the Kocher maneuver. Literature reports that traction-countertraction techniques may cause less pain than other techniques in some cases.

Image source: https://www.sciencedirect.com/science/chapter/edited-volume/abs/pii/B9780323763004000175
POST-REDUCTION EVALUATION
After the reduction is complete, it is essential to ensure that the joint is properly positioned. Therefore, a control radiographic examination is usually performed. The neurovascular examination performed before the reduction should also be repeated.
At this stage, the axillary nerve is carefully evaluated because it is one of the most frequently affected nerves in shoulder dislocations. Sensory loss or weakness in abduction on the outer side of the shoulder may suggest nerve damage.
TREATMENT: SURGERY OR CONSERVATIVE?
The treatment approach for traumatic anterior shoulder dislocation is determined by several factors, including the patient's age, activity level, concomitant injuries, and risk of recurrent dislocation. The primary goal of treatment is to restore shoulder stability, reduce pain, and minimize the risk of future recurrent dislocations.
In the acute phase, the first step is reduction and short-term immobilization. Post-reduction treatment approaches are generally divided into two main groups: conservative treatment and surgical treatment . The choice of method depends on the patient's individual risk factors and the degree of structural damage to the joint.
CONSERVATIVE TREATMENT
Conservative treatment is often preferred in patients experiencing their first shoulder dislocation and with a low risk of recurrence . This approach is considered a suitable option, especially in elderly patients or individuals with low levels of physical activity.
The key components of conservative treatment are short-term immobilization after reduction, followed by a physiotherapy program . Immobilization is generally recommended for approximately three to four weeks. This is followed by a rehabilitation program to restore range of motion in the shoulder joint and, in particular, strengthen the rotator cuff muscles.
Age is one of the most important variables determining the risk of recurrent dislocation. Studies show that the risk of recurrent dislocation decreases significantly with age. Therefore, successful results can often be achieved in elderly patients without the need for surgical treatment .
However, if the patient experiences a recurrence of dislocation or persistent instability despite conservative treatment, surgical stabilization should be considered.
SURGICAL TREATMENT
In some patient groups, the risk of recurrent dislocation after traumatic shoulder dislocation is quite high. Therefore, early surgical treatment should be considered in these patients. It is known that recurrent instability rates are high, especially in young and physically active patients, following conservative treatment . Studies have reported that in young male patients, the instability rate can reach up to 70% in a five-year follow-up after conservative treatment . Therefore, surgical stabilization may be planned earlier in athletes involved in contact sports or individuals with high activity levels.
The primary goal of surgical treatment is to restore stability to the shoulder joint and reduce the risk of re-dislocation . Today, most of these procedures can be performed arthroscopically, meaning through small incisions. The surgical technique to be used is determined by the type of injury and the degree of bone loss.
One of the most frequently performed surgical methods is arthroscopic Bankart repair . In Bankart lesions, which are common in traumatic shoulder dislocations, the labrum in the anterior-inferior part of the glenoid is torn. During this procedure, the torn labrum is re-fixed to the edge of the glenoid using special suture anchors. This restores the normal anatomy of the joint and increases shoulder stability.

Image source: https://www.fortworthorthopedics.com/bankart-repair-orthopedic-sports-medicine-specialist-fort-worth-tx.html
In patients with more pronounced bone loss or chronic shoulder instability, the Latarjet procedure may be preferred. In this method, the coracoid process on the scapula is cut and transferred to the anterior edge of the glenoid. This provides both bone support and dynamic stability through the transfer of muscle-tendon structures . The Latarjet procedure is considered a highly effective stabilization method, especially in patients with significant glenoid bone loss .

The choice of surgical method depends on many factors, including the patient's age, activity level, the extent of bone loss, and any accompanying injuries. Therefore, treatment planning is usually determined as a result of an individual assessment.
CONCLUSION
Traumatic anterior shoulder dislocation is one of the most common joint dislocations in the human body and poses a significant clinical problem, particularly in young, physically active individuals. The injury typically results from trauma to the arm in abduction and external rotation positions and is often accompanied by other injuries such as Bankart lesion or Hill-Sachs lesion.
In the acute phase, the first step in treatment is to place the humeral head into the glenoid cavity as soon as possible. The post-reduction treatment approach is determined by the patient's age, activity level, and the characteristics of any concomitant injuries. While conservative treatment may often suffice in patients with a low risk of recurrence, surgical stabilization may be a more appropriate option in younger individuals with high activity levels.
Today, surgical methods such as arthroscopic Bankart repair and Latarjet technique offer effective options for treating shoulder instability. However, the optimal treatment approach for traumatic anterior shoulder dislocation often requires careful evaluation of patient-specific risk factors.
In conclusion, accurate diagnosis, early intervention, and an individualized treatment plan play a key role in reducing the risk of recurrent instability in the management of traumatic anterior shoulder dislocation.
References:
Goth AP, Klug A, Gosheger G, Hiort ML, Akgün D, Schneider KN. Traumatic Anterior Shoulder Dislocation: Epidemiology, Diagnosis, and Treatment. Dtsch Arztebl Int. 2025 Feb 21;122(4):89-95. doi: 10.3238/arztebl.m2024.0254. PMID: 39836468; PMCID: PMC12439206.
https://www.sciencedirect.com/science/chapter/edited-volume/abs/pii/B9780323763004000175
https://musculoskeletalkey.com/injuries-in-contact-athletes/
https://www.kenhub.com/en/library/anatomy/the-shoulder-joint


Comments